Contraception - Birth Control
Summary: NuvaRing (vaginal ring)[used continuously] or Amethyst (continuous OCP) or Seasonique (extended cycle OCP) preferred in migraine without aura. Slynd progestin-only pill (POP) preferred for migraine with aura.
Contraception in Women with Migraine
CDC U.S. MEC 2024 framework • MEC = Medical Eligibility Criteria, a safety guide created by WHO and adapted by CDC (U.S. MEC) • migraine-focused preferences
Migraine WITHOUT aura • especially menstrual migraine
CHC (combined hormonal contraceptive) = MEC 2* (advantages outweigh risks)Menstrual migraine benefit: continuous use suppresses cycling and avoids estrogen withdrawal. Ring, patch, or continuous oral CHC (combined hormonal contraceptive) can accomplish this.
Continuous etonogestrel/ethinyl estradiol vaginal ring (NuvaRing/generic) — replace every 3 weeks without a hormone-free interval.
- Patch: NuvaRing is preferred but if rejected, second choice is Xulane continuously — change patch every 7 days, no patch-free week.
- If ring and patch is declined LoSeasonique-type COC preferred: levonorgestrel 0.1 mg / ethinyl estradiol 20 µg daily. Continuous regimen: Take 1 active combination tablet daily continuously. Skip the 7 low-dose EE-only tablets at the end of each pack and immediately begin the active combination tablets of the next pack. Breakthrough bleeding/spotting is common initially. Alternative: Amethyst/generic (levonorgestrel 90 µg / ethinyl estradiol 20 µg), FDA-approved for continuous daily use with no hormone-free interval.
Migraine WITH aura; Migraine WITHOUT AURA if no menstrual migraine
WITH aura: CHC (combined hormonal contraceptive with estrogen) = MEC 4 — do not useWITHOUT aura and no menstrual migraine: CDC still classifies CHC as MEC 2; the progestin-only and IUD options below are a practice preference here, not a CDC contraindication.
- norethindrone or norgestrel POP (progestin-only pill) other than Slynd, such as Opill - available without prescription but Slynd preferred
- LNG-IUD Mirena
- etonogestrel implant Nexplanon
- Depo-Provera depot medroxyprogesterone acetate (DMPA)
- copper IUD
*CDC's migraine-without-aura CHC classification assumes no other major stroke-risk condition that independently changes eligibility; evaluate the whole patient.
Migraine Aura
Aura: A fully reversible focal neurologic symptom, usually visual, sensory, or speech/language, that typically develops gradually over ≥5 minutes and lasts 5–60 minutes. Typical visual aura includes an expanding scintillating scotoma, zig-zag/fortification pattern, or spreading visual-field defect.
Usually NOT aura: Nonspecific blurred vision, floaters, brief flashes/spots, photophobia, difficulty focusing, visual symptoms lasting only seconds, or generalized lightheadedness/dizziness. These should not automatically be labeled aura.
Common U.S. products & patient instructions
EPIC search: etonogestrel 0.12 mg/day + ethinyl estradiol 0.015 mg/day vaginal ring
Patch — NO aura
EPIC search: norelgestromin 150 mcg/day + ethinyl estradiol 35 mcg/day transdermal patch
EPIC search: levonorgestrel 120 mcg/day + ethinyl estradiol 30 mcg/day transdermal system
Preferred oral option when aura is present
EPIC search: drospirenone 4 mg tablet
EPIC search: norethindrone 0.35 mg tablet
EPIC/search if documenting: norgestrel 0.075 mg tablet
LARC Long-Acting Reversible Contraception / injection (aura or no aura)
EPIC workflow: these are generally ordered through the contraception/family-planning procedure workflow rather than as a routine outpatient pharmacy prescription. Select the exact device/injection supported by your local preference list and follow the institution's insertion/administration order set.
Migraine medication interaction check
| Medication | What matters | Practical contraception approach |
|---|---|---|
| Topiramate | CDC groups topiramate with anticonvulsants that can reduce effectiveness of CHCs and certain progestin-only methods. CHC = MEC 3 for the interaction. | Prefer a method not dependent on affected hormone levels for long-term therapy (e.g., copper IUD or DMPA). LNG-IUD is not meaningfully affected by enzyme induction. If a COC is chosen, CDC specifies ≥30 µg EE. Evidence for ring/patch interactions is less certain. |
| Carbamazepine, oxcarbazepine, phenytoin, phenobarbital/barbiturates, primidone | Enzyme induction can reduce hormonal contraceptive effectiveness. | Prefer copper IUD, LNG-IUD, or DMPA (MEC 1). Implant is MEC 2 (acceptable; some reduction in levels possible). Avoid relying on POP or CHC (MEC 3). |
| Lamotrigine monotherapy | Estrogen-containing COCs can substantially lower lamotrigine concentrations; levels can rise during hormone-free intervals. | Avoid creating large estrogen cycling when seizure/mood control depends on stable lamotrigine exposure; coordinate dosing/monitoring when CHC is used. Progestin-only or IUD methods simplify this interaction. |
Important: do not reduce the topiramate issue to a ≥200 mg/day cutoff in the clinic guide. The CDC MEC recommendation is drug-based; dose-dependent PK evidence can inform individual counseling but does not replace the MEC classification.
Before prescribing estrogen
- Confirm aura.
- Check blood pressure and smoking.
- Review VTE/stroke history, thrombophilia and other vascular risks.
- Review migraine drugs for contraceptive interactions.
- New focal neurologic symptoms or a marked headache-pattern change warrants reassessment.
Primary references
CDC U.S. Medical Eligibility Criteria for Contraceptive Use, 2024; CDC U.S. Selected Practice Recommendations, 2024; current FDA/DailyMed labeling for NuvaRing/EluRyng, Xulane, Twirla, Slynd, norethindrone POPs, and Opill.
Estrogen-progestin contraceptives - Only for Migraine Without Aura
| Factor | NuvaRing | COCPs - Amethyst (Continuous Use) and Seasonique (Extended Cycle) |
|---|---|---|
| Hormonal Stability | Provides steady hormone release but requires consistent replacement. | Eliminates hormone-free intervals with continuous use. |
| Ease of Use | Inserted once every three weeks; more forgiving for missed replacements. | Requires daily adherence for effectiveness. |
| Estrogen Withdrawal | Can be used continuously to avoid withdrawal. | Designed for continuous use to prevent withdrawal. |
Continuous or Extended Cycle OCPs - Amethyst vs. Seasonique
| Feature | Amethyst (Continuous Use) | Seasonique (Extended Cycle) |
|---|---|---|
| Mechanism | Provides a steady level of hormones with no placebo pills, eliminating menstrual periods entirely. | Reduces the number of periods to four per year, with 84 days of active pills followed by 7 days of low-dose estrogen. |
| Advantages for Menstrual Migraine |
|
|
| Potential Drawbacks |
|
|
Considerations
- Continuous dosing (ie, without placebo week) of estrogen-progestin oral pills
- Continuous dosing with Nuva Ring vaginal rings (transdermal contraceptive patches are not advised for continuous dosing regimens).
- Use of estrogen-progestin oral pills with ultralow (10 to 15 micrograms) or low doses (20 to 30 micrograms).
- Use of extended-cycle preparations that reduce the number of withdrawal bleeds to four per year.
Hormonal Contraceptive Vaginal Rings – Continuous Use
NuvaRing, EluRyng (generic), Haloette (generic) (ENG/EE)
Common Adverse Reactions (≥ 2%): headache (including migraine) 11.2%
I can prescribe. Affordable Care Act (Obamacare) -- most insurance plans must cover all methods of birth control with little or no cost, including the ring.
Extended ring regimen up to 1 year: prior ENG/EE ring is removed and a new ring is immediately inserted every three weeks.
Annovera (SA/EE)
Common Adverse Reactions: Headache, including migraine 38.6%
Because incidence of headache in clinical trials was so high (greater than OCPs), I believe NuvaRing is a better choice.
Continuous use for menstrual suppression
| Feature | NuvaRing | Annovera |
|---|---|---|
| Hormones | Etonogestrel (progestin) and ethinyl estradiol (estrogen) | Segesterone acetate (progestin) and ethinyl estradiol (estrogen) |
| Usage Duration | Monthly: Inserted for 3 weeks, removed for 1 week, then replaced | Year-long: Inserted for 3 weeks, removed for 1 week, and reused for 13 cycles |
| Reusability | Single-use | Reusable for one year |
| Storage Requirements | Requires refrigeration before dispensing; can be stored at room temperature for up to 4 months | No refrigeration needed; stored at room temperature throughout its lifespan |
| Cost | Lower upfront cost; requires monthly refills | Higher upfront cost; lasts a full year |
| Convenience | Requires monthly replacement and prescription refill | Low-maintenance; no need for monthly replacement |
| Eco-Friendliness | Generates more waste (monthly replacement) | Less waste (reusable for a year) |
| Incidence of Headache | Approximately 9.8% | Approximately 38.6%, including migraines |
| Effectiveness | Similar efficacy; less than 1% pregnancy rate with typical use | Similar efficacy; less than 1% pregnancy rate with typical use |
| Side Effects | Nausea, headaches, breast tenderness, mood changes, vaginal irritation | Nausea, headaches (higher rate), breast tenderness, mood changes, vaginal irritation |
Birth Control Patche (Transdermal Systems) - Not Recommended for Migraine Because Dose of Estrogen is Higher
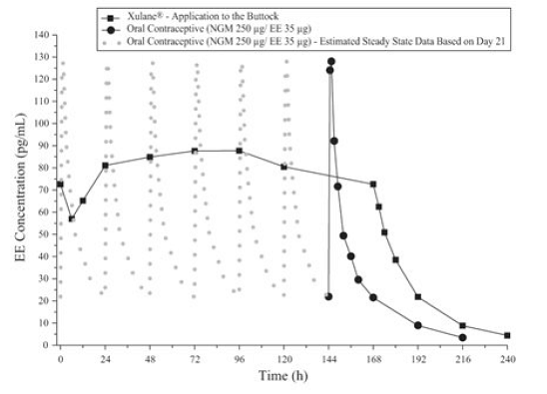
Xulane
- norelgestromin and ethinyl estradiol patch (Mylan Pharmaceuticals Inc.)
- (Generic of Ortho Evra, which has been discontinued.)
- Transdermal system: 150 mcg/day norelgestromin and 35 mcg/day ethinyl estradiol
- Xulane uses a 28-day (4-week) cycle. Apply a new patch to the upper outer arm, abdomen, buttock or back each week for 3 weeks (21 total days). Week 4 is patch-free. Apply each new patch on the same day of the week. Wear only one patch at a time.
- Contraindicated: headaches with focal neurological symptoms or have migraine headaches with aura; women over age 35 with any migraine headaches
- Pregnancy rate in women aged 18 to 35 years was 1.07 (95% CI: 0.60-1.76) per 100 woman-years
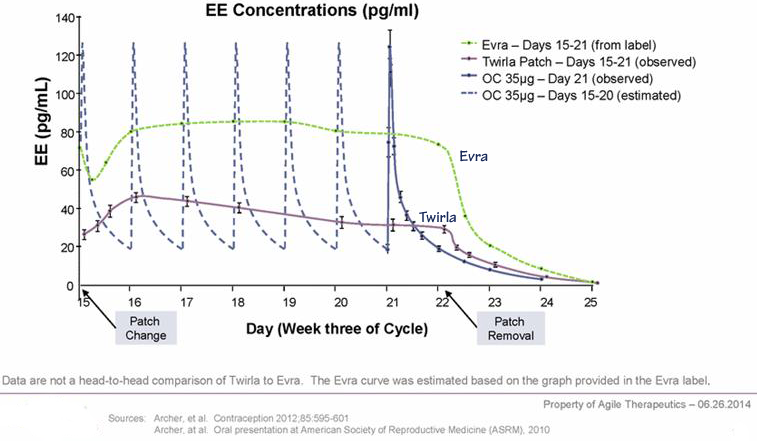
Twirla (levonorgestrel & ethinyl estradiol) transdermal system
- Second transdermal contraceptive patch available in the U.S.
- Daily hormone exposure is similar to that with oral contraceptives containing 30 mcg of ethinyl estradiol and 120 mcg of levonorgestrel
- Low dose; not clear if this provides reduced risk venous thromboembolism (VTE), which is one of the most significant safety concerns associated with combined hormonal contraceptive use
- Pearl Index (PI) measures the pregnancy rate per 100 women-years of drug exposure. Twirla's PI was 5.83, which exceeds Xulane. Obese women (BMI ≥30kg/m2) = 8.64; non-obese women 4.34.
- Contraindicated in women with a BMI >30 kg/m2.
- Contraindicated in women who have headaches with focal neurological symptoms or have migraine headaches with aura, and in women over age 35 years who have migraine headaches with or without aura.
Stroke Risk
- Risk of ischemic stroke in women with migraine is about 2 times higher than that of women without migraine, driven
largely by increased risk in the subgroup of women who have migraine with aura. - An association between migraine and an approximately 1.5 times increased risk of hemorrhagic stroke has also been shown.
- Greatest increase in stroke risk is seen in women with migraine in their reproductive years, who are under the age of 45, and who otherwise have few stroke risk factors. The elevation in risk of stroke is amplified by other risk factors, particularly smoking.
- Combined hormonal contraceptives with low estrogen probably have reduced stroke risk (low estrogen OCPs: 20-25 µg ethinyl estradiol; average 35 µg; some as low as 10 µg)
- Absolute risk of stroke in reproductive-aged women is low (3.56 per 100,000 women of reproductive age per year)
Relative increased ischemic stroke risk about 3-fold
- 20 µg EE 1.6 (not clear that risk is increased)
- 30-49 µg EE 2.0 (no clear that risk is increased
- >49 µg EE 2.4 (clear increased stroke risk)
One study differentiated risk by presence or absence of migraine aura and found an increased risk in the migraine with aura population (OR 6.1 in migraine with aura vs 1.8 migraine without aura group).
Progestin-only Pill (POP) - For Patients with Migraine with Aura
| Name | Active Ingredient | Availability | Notes |
|---|---|---|---|
| Opill | 0.075 mg of norgestrel | Over-the-Counter (OTC) | First OTC progestin-only contraceptive, available since 2023. |
| Slynd | 4 mg of drospirenone | Prescription | Newer option with a 24-active plus 4-inert pill regimen. |
| Nora-BE | 0.35 mg of norethindrone | Prescription | Traditional progestin-only contraceptive. |
| Camila | 0.35 mg of norethindrone | Prescription | Another traditional progestin-only option. |
| Errin | 0.35 mg of norethindrone | Prescription | Part of the traditional progestin-only contraceptives. |
| Feature | Slynd (Drospirenone) | Other POPs (Norethindrone) |
|---|---|---|
| Progestin Type | Drospirenone | Norethindrone |
| Regimen | 24 active + 4 placebo | Continuous active (28 pills) |
| Missed Pill Window | 24 hours | 3 hours |
| Androgenic Effects | Anti-androgenic, reduces acne | Androgenic, may exacerbate acne |
| Fluid Retention | Reduces bloating and retention | No diuretic effect |
| Suitability | Flexible use, special populations | Strict timing required |
- Anti-Androgenic Effects:
- May improve conditions like acne or hirsutism (excess hair growth).
- Less likely to exacerbate androgen-related side effects, such as oily skin or hair loss.
- Anti-Mineralocorticoid Effects:
- Reduces fluid retention and bloating, offering potential benefits for individuals sensitive to water retention.
- May slightly lower blood pressure.
-
Missed Pill Window:
- Slynd: Offers a 24-hour missed pill window, meaning contraceptive protection is maintained even if a dose is taken up to 24 hours late. This flexibility can reduce missed doses and improve real-world efficacy.
- Other POPs: Require doses to be taken within a 3-hour window daily, making them less forgiving and more prone to user error.
- Slynd: Suppresses ovulation more consistently (~99% of cycles), akin to combination birth control pills. This adds a layer of protection beyond the cervical mucus-thickening mechanism.
- Other POPs: Do not consistently suppress ovulation and rely more heavily on thickened cervical mucus and endometrial changes for contraception.